thymosin alpha 1 in sepsis and pancreatic trials
The pancreatic trials
Thymosin alpha 1 was studied during severe acute pancreatitis because these patients can face infectious complications as well as inflammation. A meta-analysis of 5 randomized trials with 706 patients found fewer infections outside the pancreas, with a risk ratio of 0.56. The corresponding ratios were 0.60 for bloodstream infections and 0.38 for abdominal infections. A risk ratio below one favours the treatment group in these comparisons.
The review also reported higher CD4+ T-cell measurements and an improved CD4+/CD8+ ratio. Hospital stay length showed no improvement. I regard the infection outcomes as the reason to take the paper seriously; the immune measurements help describe what happened alongside them.
There are only five trials in that pool. The result supports further investigation of a particular complication in a particular illness. It leaves the broader claim of reliable immune protection a long way from settled.
ETASS: the early sepsis signal
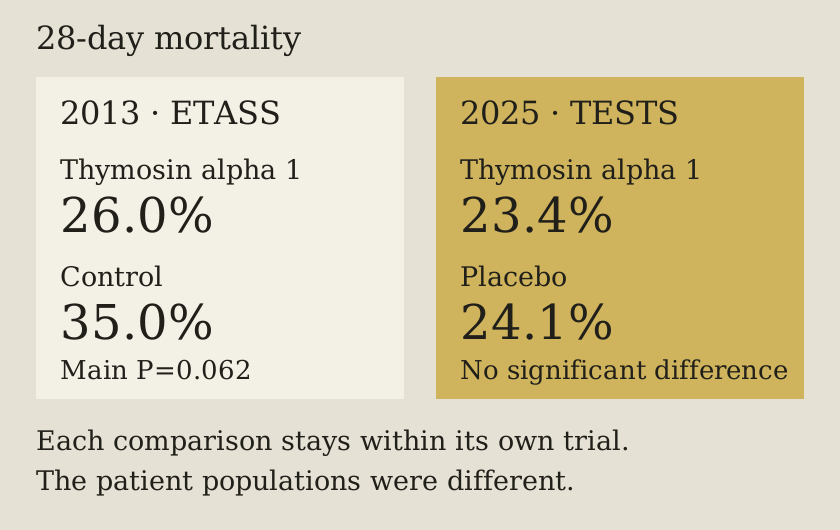
Sepsis is a dangerous response to infection that can damage organs. Its immune disturbances gave investigators a reason to test thymosin alpha 1. In the 2013 ETASS randomized trial, 28-day mortality was 26.0% with the peptide and 35.0% in controls.
That numerical gap is often the headline. The main mortality analysis had P=0.062, which did not meet the conventional threshold for statistical significance. In-hospital mortality was 28.7% versus 39.4%, with P=0.032. The different analyses deserve to travel with the encouraging percentages.
Monocyte HLA-DR, a surface marker used to assess immune activity, improved on days 3 and 7. The biology was moving in the hoped-for direction. Survival still needed a firmer answer.
The 2016 sepsis review
A 2016 systematic review pooled 19 randomized trials involving 1,354 patients. It reported lower 28-day mortality with thymosin alpha 1, with a risk ratio of 0.59, alongside changes in lymphocyte groups and inflammatory signalling.
Pooling trials can make a pattern easier to see. It also carries the limitations of the contributing studies forward. The pooled result explains the early optimism. A large blinded trial would put the survival claim under a different degree of pressure.
The larger TESTS trial
The 2025 TESTS trial was double blinded and placebo controlled: patients and staff did not know which treatment had been assigned. It enrolled 1,106 adults with sepsis across 22 centres. At 28 days, mortality was 23.4% with thymosin alpha 1 and 24.1% with placebo. The hazard ratio was 0.99, with P=0.93. The overall survival benefit had failed to appear.
Age and diabetes subgroups raised questions for further work. They did not establish a patient group with a proven benefit. For me, the broad sepsis indication loses its footing here; rescuing it would require a new, prospectively defined test.
The pancreatic infection review and TESTS address different illnesses and outcomes. Neither can erase the other. The productive next step is to specify the immune state and clinical outcome being investigated before the trial begins.
Thymosin alpha 1 mechanism of action
The TA-1 peptide is studied at the meeting point between immediate immune defences and the more specialised T-cell response. A review of its immune signalling describes dendritic-cell maturation and Toll-like receptor pathways. Toll-like receptors help immune cells recognise signs of a threat; their involvement supplies a plausible route from the peptide to altered immune activity.
One experiment gives that mechanism a more tangible shape. Human macrophages grown in the laboratory took up and killed fungal material more effectively after thymosin alpha 1 exposure, within 30 minutes of challenge, without inducing the inflammatory signals TNF-alpha or IL-6. These were human-derived cells in a dish. The finding describes a cellular response, and a clinical trial must still establish the outcome in patients.
That distinction gives the acute-care story its tension. A drug can influence an immune process and still fail to improve survival in the population enrolled. TESTS is a particularly clear reason to resist finishing the clinical story from the mechanism alone.